If you’re experiencing ongoing pelvic pain, you’re not alone. Chronic pelvic pain (discomfort in the lower abdomen lasting six months or longer) affects many people, especially women, and can significantly impact day-to-day life. It is also often frustrating to get to the bottom of. Many people see several doctors, get several tests, and still don’t have a clear answer.
One cause that frequently gets missed is a group of conditions called pelvic venous disorders, problems with the veins in the pelvis and abdomen.
I wrote a guide on these conditions for Canadian Family Physician, the journal read by family doctors across Canada, to help them recognize and manage them. This post is a plain-language version of that guide, so patients can understand the same information. My goal here is to help you recognize when a venous cause is worth considering and understand how it’s diagnosed and treated. It is not a substitute for seeing your own doctor.
What are pelvic venous disorders?
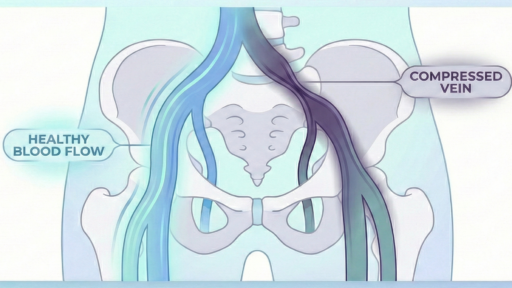
Veins carry blood back toward the heart. When the veins in the pelvis don’t work properly (either because blood flows backward or because a vein is squeezed shut) blood can pool and pressure can build up. That pressure causes the symptoms.
Conditions you may have heard of by older names (pelvic congestion syndrome, nutcracker syndrome, May-Thurner syndrome) are now understood as part of this single family of pelvic venous disorders. They show up in four main ways:
Kidney-area symptoms (from left renal vein compression). When the vein draining the left kidney is squeezed, it can cause back pain, blood in the urine, and sometimes protein in the urine that appears when standing. The older name for this is nutcracker syndrome.
Chronic pelvic pain of venous origin. This is the classic presentation, most often in women aged 20 to 45 who have had more than one pregnancy. The pain is typically a dull ache, not linked to the menstrual cycle, that gets worse with standing or through the day, and sometimes after intercourse. The old name was pelvic congestion syndrome.
Varicose veins in unusual places. Because of pelvic vein reflux, varicose veins can appear on the vulva, perineum, or thighs. Importantly, some leg varicose veins actually start from a pelvic source and if that source is missed treatment aimed only at the leg can fail.
Leg symptoms from a squeezed vein (venous claudication). When the left iliac vein in the pelvis is compressed, it reduces outflow from the left leg, causing swelling, aching with walking, varicose veins, or blood clots. The older name is May-Thurner syndrome.
Why these get missed
Chronic pelvic pain has a long list of possible causes: endometriosis, interstitial cystitis, irritable bowel syndrome, fibromyalgia, nerve entrapment, muscle and joint pain, and others. Pelvic venous disorders sit on that list but are often overlooked, especially when earlier gynaecologic tests come back normal.
A few clues raise the suspicion of a venous cause: pelvic pain that is dull, unrelated to the menstrual cycle, worse with standing, in someone who has had multiple pregnancies, and who may have varicose veins around the perineum. One useful sign described in the literature is tenderness over a specific point on the lower abdomen. When combined with pain after intercourse these are fairly good at pointing toward a venous cause rather than another one.
How Are Pelvic Vein Problems Diagnosed?
If your doctor suspects a problem with your pelvic veins, they may recommend imaging tests, such as ultrasound or MRI scans, to get a closer look at what’s happening inside your body. Ultrasound, in particular, is a great tool for seeing if there are any problems with your veins, such as compression or blood pooling.
By diagnosing these conditions early, your doctor can help create a personalized treatment plan that will give you the best chance of relief.
How pelvic venous disorders are treated
Not everyone with a pelvic vein abnormality needs treatment. Many people have findings on imaging and no symptoms at all. When symptoms are real and linked to the veins, treatment is matched to the specific problem (reflux, renal vein compression, or iliac vein obstruction), and someone with more than one problem may need a combination of approaches.
Medications have been tried (certain hormone therapies, and a vein-targeted supplement called micronized purified flavonoid fraction) but their benefits are limited, often fade after stopping, and they’re not a mainstay of treatment.
For pelvic pain from reflux: embolization. The most common and guideline-supported treatment is coil embolization: tiny coils are placed in the faulty veins (often the ovarian veins) to block the backward flow. Studies from several countries report that most patients get substantial or complete relief, with benefits lasting years. Sclerotherapy (injecting a medicine that collapses a vein) is often used alongside it.
For varicose veins from a pelvic source. When the problem is mainly visible varicose veins without significant pelvic pain, guidelines favour treating the veins locally (for example, foam sclerotherapy) rather than jumping to pelvic embolization. Embolization is reserved for people who actually have pelvic symptoms.
For a blocked or squeezed iliac vein: stenting. When a vein is significantly obstructed and symptoms are severe, opening it with a stent is the recommended first-line treatment. It can relieve both the pelvic and the leg symptoms. (See my guide to [iliac vein stent recovery].)
For renal vein (nutcracker) compression. This is the most complex to treat and usually needs a multidisciplinary team. Both surgery and, more recently, stenting have been used. Stenting can give quick relief, but it carries specific risks in this location which is why these decisions are made carefully and individually.
Living with Chronic Pelvic Pain
Living with chronic pelvic pain can be challenging, but there are ways to manage it. Working with a team of healthcare providers, including doctors, physical therapists, and mental health professionals, can help you find the right combination of treatments to improve your quality of life.
The bottom line
Pelvic venous disorders are common, treatable, and frequently missed as a cause of chronic pelvic pain and varicose veins, especially in women who’ve had multiple pregnancies. Recognizing the pattern, confirming it with the right imaging, and matching treatment to the specific problem can substantially improve symptoms and quality of life. If the picture in this post sounds like yours, it’s a reasonable thing to raise with your doctor.
Not sure how to bring this up with your doctor? See how to talk to your doctor about venous compression.
Frequently asked questions
The most common is chronic pelvic pain that is a dull ache, unrelated to the menstrual cycle, and worse with standing or by the end of the day, often in women who have had more than one pregnancy. Other signs include varicose veins on the vulva, perineum, or thighs; leg swelling or aching; back pain or blood in the urine (from kidney-vein compression); and pain after intercourse.
Usually in steps. A Doppler ultrasound (through the abdomen and often internally) is the first test, looking for widened veins and backward blood flow. If results are unclear, CT or MRI gives a more detailed map. Venography, a thin-tube test from inside the vein, is the most precise and is usually reserved for unclear cases or done just before treatment.
Yes, and treatment is often very effective for significant symptoms. The approach is matched to the problem: coil embolization for pelvic pain from reflux, local treatments for varicose veins from a pelvic source, and stenting for a blocked or squeezed iliac vein. Renal vein compression is more complex and needs a multidisciplinary team.
Not necessarily. A squeezed iliac vein is found in roughly a quarter to a third of people who have no symptoms at all. So a compression seen on imaging always has to be interpreted alongside your symptoms and exam, it isn’t proof of the cause on its own. This is why careful assessment matters.